When your baby or young child develops a mysterious rash, belly pain, reflux, or unexplained fussiness, it’s easy to wonder if it could be related to something they’re eating.
You’re not alone in asking this question. Many parents suspect that their child’s symptoms may be related to a food, but studies show that food allergies are diagnosed much less often than they are perceived.
What’s the reason for this? Infant and childhood symptoms can be confusing, and many common childhood issues, including viral infections, can look similar to a food allergy.
This article will help you understand what a food allergy really is, how to recognize the signs of a classic allergic reaction, why some common symptoms can have other causes, and what steps to take if you suspect your child has a food allergy.
What Is a Food Allergy?
Let’s start with a clear definition.
A food allergy is an immune system reaction to a protein in a food.
In someone with a food allergy, the body mistakenly identifies a food protein as harmful and mounts a response when the food is eaten. This response can affect multiple parts of the body, including the skin, respiratory system, gastrointestinal tract, and cardiovascular system.
Not every adverse reaction to food is a food allergy. Food can cause a variety of reactions that are not immune related, including food intolerances, and other conditions that affect digestion. These reactions can cause real, and sometimes significant symptoms, but they are different from a food allergy.
This article focuses specifically on food allergies.
The 2 Main Types of Food Allergy
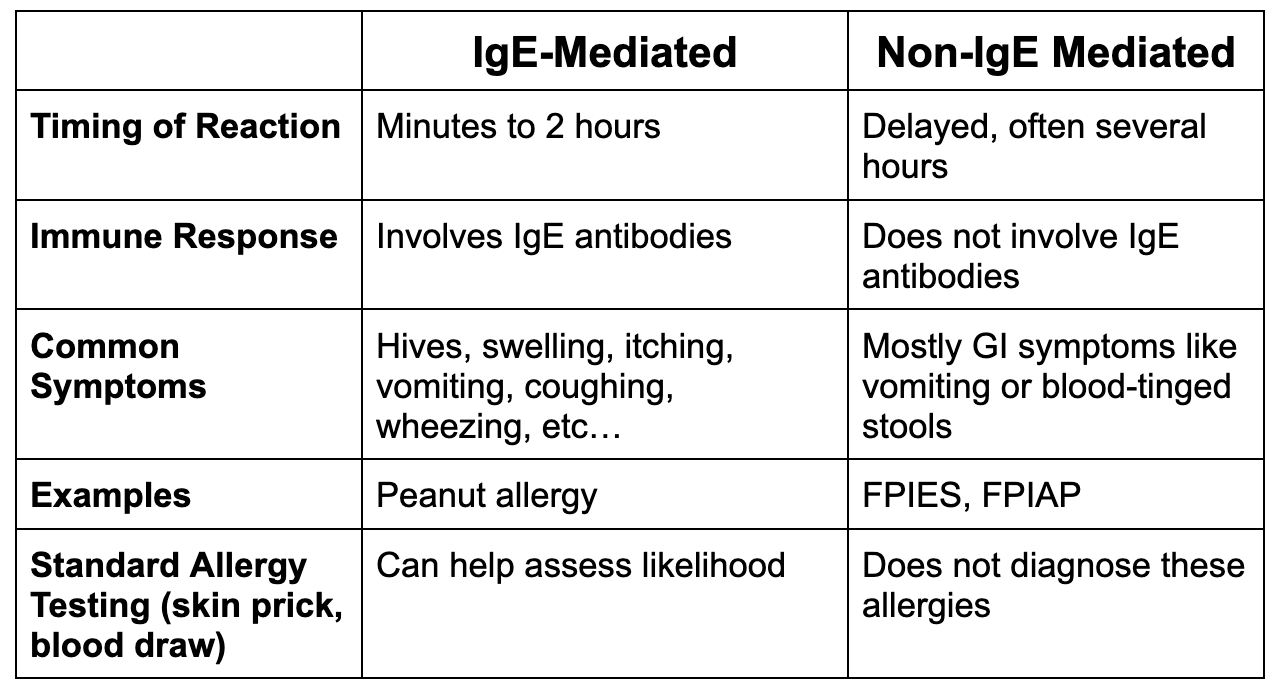
Food allergies are generally grouped into two major categories based on how the immune system responds to the food: IgE-mediated and non-IgE mediated.
Non-IgE mediated allergies can sometimes be hard to spot because they don’t follow classic food allergy symptoms and timing of these reactions can be delayed.
What an IgE-Mediated Food Allergy Looks Like
IgE-mediated food allergies are what many people think of when they hear the term “food allergy.” They typically cause symptoms quickly after eating the food, often within minutes and usually within 2 hours.
A consistent pattern is an important clue. When a child has an IgE-mediated food allergy, similar symptoms occur every time they eat the triggering food.
Symptoms can affect different parts of the body:
Skin
Hives
Itching
Swelling of the lips, tongue, or face
Mouth and throat
Itchy mouth or throat
Throat tightness or swelling
Breathing
Coughing
Wheezing
Trouble breathing
Digestive system
Nausea
Vomiting
Abdominal pain
More serious reactions can involve dizziness, fainting, or other signs of a drop in blood pressure and may indicate anaphylaxis, a severe allergic reaction that requires immediate medical attention.
The symptoms of an IgE-mediated reaction generally resolve within a few hours after the reaction is treated or the exposure ends. Unlike many other childhood conditions, IgE-mediated food allergies cause a reproducible reaction after exposure, rather than chronic symptoms that continue day after day without eating the food.
Symptoms that Don’t Always Mean Food Allergy
Some symptoms can look like a food allergy but are often caused by something else. Understanding the pattern of your child’s symptoms can help you know when food allergy is more likely and when another explanation may make more sense.
Eczema
Eczema and food allergy are closely connected, but eczema does not automatically mean that a food is causing your child's skin symptoms.
Children with moderate-to-severe eczema are more likely to have a food allergy. When they do, eating the food they're allergic to usually causes an immediate reaction, such as hives, swelling, or vomiting, rather than just an eczema flare.
Food triggers eczema flares in only a small subset of children, most commonly with egg or cow's milk. But eczema is primarily a skin condition and is treatment includes good skin care with appropriate moisturizers and topical treatments. Removing foods does not fix the underlying skin barrier defect.
It's important not to eliminate foods unnecessarily. A child who previously tolerated a food can develop an IgE-mediated food allergy after a period of avoidance, potentially leading to a more serious reaction when the food is eaten again.
If you suspect a food is contributing to your child's eczema, talk with your child's healthcare provider before removing it from their diet.
Hives That Linger
Hives can occur for many reasons, including viral infections. When hives are caused by an IgE-mediated food allergy, they typically develop quickly after eating the triggering food and resolve within a few hours.
Hives that stick around for days, particularly when there is no consistent connection to eating a particular food, are less typical of a food allergy.
Redness Around the Mouth
Redness or irritation around the mouth can happen when foods such as tomatoes, citrus fruits, or berries come into contact with sensitive skin. This type of irritation is not necessarily an allergic reaction, especially when your child has no other symptoms, and does not react to different preparations of the same food, i.e has redness with fresh tomato but not with ketchup.
The timing and pattern of symptoms matter. If you notice a possible reaction to a food, keep track of what your child ate, how much they ate, when symptoms started, and what the symptoms looked like. This information can help your child's healthcare provider determine whether food allergy should be considered.
Understanding Your Child’s Risk Factors
Any child can develop a food allergy, but some children have a higher risk.
Moderate-to-Severe Eczema: This is the single strongest risk factor for food allergy. When an infant has inflamed, broken skin from eczema, tiny food protein particles can enter through the skin barrier, causing the immune system to become sensitized before the infant ever tastes the food orally.
Family History of Allergic Conditions: Children with a parent or sibling who has a food allergy or other allergic condition may have a higher risk of developing allergies themselves. They do not necessarily inherit the same food allergy their parent or sibling has, just the increased risk.
Other Allergic Conditions: Children who already have conditions such as asthma or allergic rhinitis may be more likely to develop food allergy.
Early-Life Environment and Microbiome Shifts: Although these factors are largely outside our control, certain conditions that can influence early gut bacteria diversity, such as cesarean birth and antibiotic exposure during the first year of life, have been associated with an increased risk of food sensitization.
Having one or more of these risk factors does not mean your child has a food allergy. It simply means their risk may be higher.
What About Introducing Allergenic Foods?
We now know that routinely delaying allergenic foods does not prevent food allergy. Current guidance supports introducing age-appropriate forms of common allergens during infancy rather than avoiding them unnecessarily.
For infants with severe eczema or other risk factors, talk with your child's doctor about the best way to introduce allergenic foods safely.
How Is a Food Allergy Diagnosed?
If you suspect your child has a food allergy, the diagnosis should be made by a qualified physician, often starting with your child's pediatrician. Your pediatrician can evaluate the symptoms and clinical history and help determine the next steps, which in many cases will lead to an allergist referral.
Your child's clinical history is one of the most important pieces of the puzzle. What they ate, how much they ate, what symptoms occurred, and how quickly those symptoms appeared can help their healthcare provider determine whether a food allergy is likely.
Testing may be part of the evaluation, but a test result alone cannot diagnose a food allergy.
Testing Looks for Sensitization
Skin prick tests and blood tests measure whether your child's immune system recognizes a particular food. This is called sensitization. A child can be sensitized to a food without actually having an allergic reaction when they eat it.
This is why broad food allergy panels can lead to unnecessary food restrictions. Test results need to be interpreted alongside your child's symptoms, the timing of the reaction, how much of the food was eaten, and other details of their history.
Sometimes an Oral Food Challenge Is Needed
When the diagnosis is unclear, an allergist may recommend a medically supervised oral food challenge. During an oral food challenge, a child eats gradually increasing amounts of the food under medical supervision while being monitored for a reaction.
When appropriate, an oral food challenge is the gold standard for determining whether a child has a food allergy.
What to Do if You Suspect a Food Allergy
If you think your child may have a food allergy, you don't have to figure it out on your own. A clear history of what happened, when it happened, and what your child ate can help guide the evaluation.
Your Parent Action Plan
1. Keep track of reactions.
Write down what your child ate, how much they ate, when symptoms started, what the symptoms looked like, and how long they lasted.
2. Talk with your child's pediatrician.
Share your concerns and your notes about the reaction. Your child's provider can help determine whether an allergy evaluation is appropriate.
3. Get help with food restrictions.
If it’s determined medically that your child needs to avoid a food or food group, a registered dietitian can help you find safe, nutritious alternatives, navigate food labels, and make sure your child continues to get the nutrients they need for healthy growth and development.
The Bottom Line
Food allergies are complex. If you have concerns about your child, talk with their doctor about appropriate evaluation and next steps. Removing foods from your child’s diet without a proper diagnosis can add unnecessary stress and increase the risk of nutritional deficiencies.
References
Boyce JA, Assa’ad A, Burks AW, et al. Guidelines for the diagnosis and management of food allergy in the United States: Report of the NIAID-sponsored expert panel. J Allergy Clin Immunol. 2010;126(6 Suppl):S1-S58.
National Academies of Sciences, Engineering, and Medicine (NASEM). Finding a Path to Safety in Food Allergy: Assessment of the Global Burden, Causes, Prevention, Management, and Public Policy. Washington, DC: The National Academies Press; 2017.
Stukus DR, Mikhail I. Pearls and pitfalls in diagnosing IgE-mediated food allergy. Curr Allergy Asthma Rep. 2016;16(5):34.
Eigenmann PA, Beyer K, Lack G, et al. Are avoidance diets still warranted in children with atopic dermatitis? Pediatr Allergy Immunol. 2020;31(1):19-26.
Kelso JM. Unproven diagnostic tests for adverse reactions to foods. J Allergy Clin Immunol Pract. 2018;6(2):362-365.
FARE Pediatric Food Allergy Course. Modules 1 & 2: Adverse Food Reactions Defined & IgE-Mediated Reactions. Food Allergy Research & Education (FARE). 2026.
Disclaimer: This article is for educational purposes only and is not intended as personalized medical advice. Always consult your child’s healthcare provider regarding your child’s specific health, medical, and nutritional needs. Last reviewed: October 2026
